- info@rkeyecenter.com
- Call Us +91-7024154321 | +91-7312705058

Retinal Detachment Treatment in Indore
Retinal detachment is a medical emergency and can be painless. Prompt examination helps a retina specialist identify a retinal tear, a partial detachment or a more extensive detachment—and plan the appropriate treatment.
Do not wait for pain. Visit a retina specialist urgently if these symptoms are new or worsening.
Symptoms That Need Immediate Attention
Seek urgent eye evaluation if you notice a sudden increase in floaters, repeated flashes of light, a dark curtain or shadow, or a sudden change in side or central vision.
New floaters
Spots, specks, cobweb-like shapes or moving shadows that appear suddenly or increase quickly.
Flashes of light
New or repeated flashes, especially in the side of your vision, should be assessed without delay.
Curtain or shadow
A dark veil, curtain or shadow moving across any part of the visual field is an urgent warning sign.
These symptoms can also occur with posterior vitreous detachment or other eye conditions. Symptoms alone cannot reliably distinguish a harmless vitreous change from a retinal tear or detachment; a dilated retinal examination is important.
What Is Retinal Detachment?
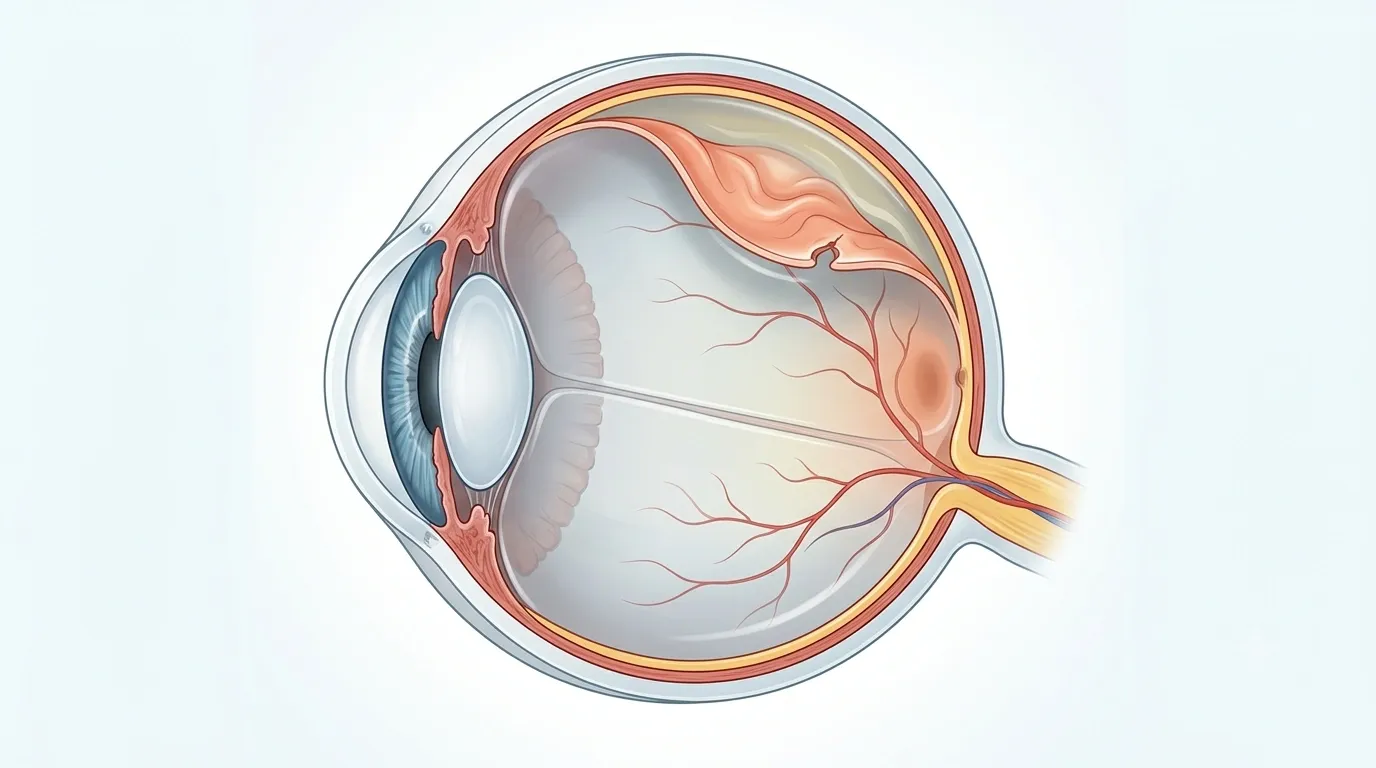
The retina is the light-sensitive layer of tissue at the back of the eye. Retinal detachment occurs when the retina separates from its normal position. Once detached, the affected retinal tissue cannot function normally, and untreated detachment can result in permanent loss of vision.
A retinal tear is not the same as a retinal detachment. A tear or hole may allow fluid to pass underneath the retina and can progress to detachment. When a suitable tear is found before significant detachment develops, laser photocoagulation or cryopexy may sometimes seal the tear and reduce the risk of progression.

Types of retinal detachment
Who Is at Higher Risk?
- High or severe myopia (high minus power)
- Previous retinal tear or retinal detachment in either eye
- Family history of retinal detachment
- Previous eye surgery, including cataract surgery
- Significant eye injury or trauma
- Posterior vitreous detachment or lattice degeneration
- Diabetic retinopathy or other retinal scarring
- Other conditions that can produce retinal traction
How Retinal Detachment Is Diagnosed
The key examination is a dilated retinal examination. The retina specialist assesses the location and extent of any retinal tear or detachment and whether the macula is involved.

Dilated fundus examination
Inspects the peripheral retina and helps identify retinal breaks.
Ocular ultrasound (B-scan)
May be recommended when the retina cannot be seen clearly, such as with vitreous haemorrhage.
OCT imaging
Provides detailed assessment of the macula or retinal layers when clinically useful.
Retinal Tear Treatment
Some retinal tears or holes can be treated before a full retinal detachment develops. The correct approach depends on the tear, its location, symptoms and retinal findings.
Laser photocoagulation
Laser spots are placed around the retinal break to create a sealing adhesion around the tear.
Cryopexy
A freezing probe is applied externally over the retinal break to create a sealing scar.
Individual decision
Not every retinal hole or tear needs the same treatment. Observation, laser, cryopexy or another approach may be advised after examination.
Repair Is Chosen for the Individual Eye
Once a clinically significant retinal detachment is present, surgical repair is often required. The objective is to close or support the retinal break, remove traction where necessary and reposition the retina.
| Procedure | What it does | When it may be considered |
|---|---|---|
| Pneumatic retinopexy | A gas bubble pushes the detached retina toward the eye wall; laser or cryotherapy seals the break. | Selected detachments where the break pattern and position are suitable. |
| Scleral buckle | A silicone band or element supports the outer wall of the eye and reduces traction. | Particular rhegmatogenous detachments, based on break pattern and surgeon assessment. |
| Pars plana vitrectomy | The vitreous gel is removed through small openings; traction is relieved and gas or silicone oil may support the retina. | Many detachments, including complex cases, vitreous haemorrhage or proliferative vitreoretinopathy. |
| Combined surgery | More than one technique is used when it offers better anatomical support. | Complex or selected cases based on retinal findings. |
What to Expect After Retinal Detachment Surgery
During vitrectomy, the surgeon removes most of the vitreous gel to access the retina and relieve traction. Laser or cryotherapy may treat retinal breaks. Air, a gas bubble or silicone oil may be placed inside the eye while it heals.
Recovery varies with the procedure, severity and duration of detachment, whether the macula was involved and the health of the retina. Vision can remain blurred early on and may improve gradually. Anatomical reattachment does not always mean vision will return to its pre-detachment level.
- Use prescribed eye drops exactly as advised.
- Attend scheduled post-operative retinal examinations.
- Follow positioning instructions if gas or oil has been used.
- Avoid strenuous activity, driving or travel until specifically cleared.

If a gas bubble is used, you may need a specific head position. Air travel and travel to high altitude can be unsafe while an intraocular gas bubble is present. Always confirm with your retina surgeon before flying, driving, exercise or resuming routine activities.
Contact RK Eye & Retina Center, Indore
Share a few details for appointment coordination. If symptoms are sudden or worsening, call the center directly rather than waiting for an online response.
Request Received
Thank you! Our team at RK Eye & Retina Center will contact you shortly to schedule your consultation.
RK Eye & Retina Center • Jaora Compound, opposite M.Y. Hospital, Indore
Book an appointment online
Frequently Asked Questions
Is retinal detachment a medical emergency?
Yes. New flashes, a sudden shower of floaters, a curtain or shadow in vision, or sudden vision loss require urgent retinal evaluation. Early treatment can help protect vision.
Can a retinal tear be treated without major surgery?
In suitable cases, a retinal tear or small hole may be treated with laser photocoagulation or cryopexy before it progresses to a retinal detachment. The decision depends on the retinal findings.
Which surgery is best for retinal detachment?
There is no single operation that is best for every retinal detachment. Pneumatic retinopexy, scleral buckle, vitrectomy or a combination may be recommended depending on the detachment pattern and the individual eye.
Will vision return completely after surgery?
Visual recovery varies. It depends on factors such as how long the retina was detached, whether the macula was involved, the underlying retinal condition and whether complications are present. Surgery aims first to reattach and stabilize the retina; the final visual outcome cannot be guaranteed.
Can retinal detachment happen again after treatment?
Yes. Re-detachment can occur, and some eyes require additional treatment or surgery. Follow-up examinations are therefore important.
Can I fly after vitrectomy or retinal detachment surgery?
If a gas bubble has been placed inside the eye, flying or travelling to high altitude may be dangerous until the gas has fully absorbed. Follow the retina surgeon’s specific instructions before air travel.
Does retinal detachment always cause pain?
No. Retinal detachment is commonly painless. Sudden visual symptoms—not pain—are the key warning signs.
Should the other eye also be checked?
Yes. A complete retinal examination of both eyes is often relevant because some risk factors can affect both eyes. Your retina specialist will advise whether preventive treatment or closer follow-up is needed in the fellow eye.
Sudden flashes, floaters or a curtain in vision?
Call RK Eye & Retina Center for urgent retina guidance in Indore.
This page is for awareness and appointment guidance. Treatment timing and procedure choice require a retinal examination.